Wolff-Parkinson-White Syndrome
Wolff-Parkinson-White syndrome describes the presence of an accessory conduction pathway connecting the atria to the ventricles associated with episodes of tachyarrhythmias.1
By convention, the finding of electrocardiographic signs of preexcitation secondary to the presence of this accessory pathway—even in the absence of clinical tachycardias or palpitations—is also commonly referred to as Wolff-Parkinson-White syndrome.
The prevalence of a Wolff-Parkinson-White pattern on ECG typically ranges between 0.15% and 0.25% of patients,2 increasing up to 0.55% among first-degree relatives of affected patients.3
Not all patients develop episodes of supraventricular tachycardia, and the finding of intermittent preexcitation is often more frequent than expected.1
Patients diagnosed with Wolff-Parkinson-White syndrome generally carry a slightly higher risk of sudden cardiac death compared to the healthy population. This risk depends on the properties of the accessory pathway.
Atrioventricular Accessory Pathway (Bundle of Kent):
As mentioned, the anatomical substrate of this condition is the presence of an accessory pathway (bundle of Kent) that electrically connects the atria to the ventricles. This bundle creates a second propagation pathway for the electrical impulse.
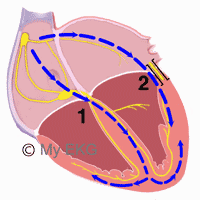
Accessory Pathway of Wolff-Parkinson-White
- 1. Normal conduction system.
- 2. Accessory pathway (bundle of Kent).
The bundle of Kent is typically composed of normal myocardial fibers and lacks the physiological delay of the AV node; thus, a portion of the ventricular myocardium depolarizes via this pathway prior to conduction through the normal conduction system.
The clinical and electrocardiographic manifestations of Wolff-Parkinson-White depend on the pathway's characteristics (conduction velocity, anterograde, retrograde, or bidirectional conduction).
Wolff-Parkinson-White Electrocardiogram
The classic Wolff-Parkinson-White ECG displays electrocardiographic signs of preexcitation.
Electrocardiographic Signs of Preexcitation
Because the impulse originates in the SA node, the P wave is normal.
In preexcitation, the ventricles depolarize from two distinct sites: the His-Purkinje system and the accessory pathway.
Depolarization via the accessory pathway usually occurs earlier, resulting in a shortened PR interval and the appearance of a delta wave at the onset of the QRS complex, leading to QRS widening.
When a high degree of preexcitation is present (greater conduction over the accessory pathway than through the normal conduction system), the QRS complex assumes a bundle branch block morphology, becoming wider and exhibiting secondary ST-segment changes and T-wave inversions.
Signs of Complete Ventricular Preexcitation in Wolff-Parkinson-White
Adapted from AHA/ACCF/HRS recommendations for the standardization and interpretation of the electrocardiogram part III: intraventricular conduction disturbances.4
The following criteria are indicative of complete preexcitation:
- Short PR interval, less than 120 ms during sinus rhythm in adults and less than 90 ms in children.
- Slurring of the initial portion of the QRS complex (delta wave), interrupting the P wave or arising immediately after its completion.
- QRS duration greater than 120 ms in adults and greater than 90 ms in children.
- Secondary ST-segment and T-wave changes.
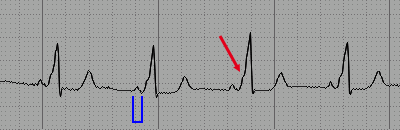
Wolff-Parkinson-White: shortened PR interval (blue), wide QRS due to delta wave (red).
Electrocardiographic Variability in Wolff-Parkinson-White
It is common for the degree of preexcitation to vary; it may differ between separate EKGs or even within the same EKG tracing.
The conduction velocity of the accessory pathway dictates the degree of preexcitation.
The greater the degree of preexcitation, the more pronounced the delta wave, the wider the QRS complex, and the more evident the repolarization abnormalities.
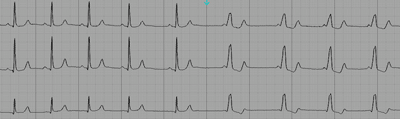
Wolff-Parkinson-White:
EKG alternating between normal beats and preexcited beats (short PR interval, wide QRS complex, T-wave abnormalities).
"Concealed" Accessory Pathways
A concealed accessory pathway is one that exhibits retrograde conduction only (from the ventricles to the atria) while retaining the capacity to mediate orthodromic AV reentrant tachycardia (see below).
Because anterograde conduction from the atria to the ventricles is absent, the characteristic features of preexcitation do not occur, rendering the sinus rhythm EKG normal.
For this reason, it is termed a "concealed" accessory pathway, as it cannot be diagnosed on a baseline sinus rhythm EKG.
Tachycardia in Wolff-Parkinson-White Syndrome
In Wolff-Parkinson-White syndrome, a macro-reentrant circuit is formed by the atria, the conduction system, the ventricles, and the accessory pathway. Atrioventricular reentrant tachycardias (AVRT) can be generated via this circuit.
Orthodromic Tachycardia:
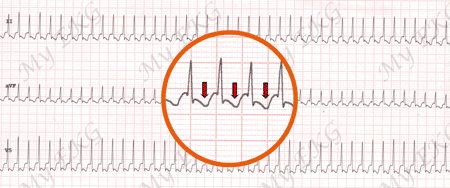
Orthodromic tachycardia at 250 bpm
Narrow QRS tachycardia; no signs of preexcitation. Retrograde P waves in red.
Orthodromic tachycardia is the most common tachycardia in Wolff-Parkinson-White, accounting for approximately 90% to 95% of supraventricular tachycardia episodes in patients with a manifest accessory pathway.5
The electrical impulse travels anterograde from the atria to the ventricles via the normal conduction system and retrograde back to the atria via the accessory pathway.5
It presents as a narrow-complex QRS tachycardia (in the absence of underlying aberrancy or block). Signs of preexcitation are not observed during tachycardia.
Antidromic Tachycardia:
Antidromic tachycardia accounts for approximately 5% of supraventricular tachycardia episodes in patients with a manifest accessory pathway.5
In this tachycardia, the impulse travels anterograde from the atria to the ventricles via the accessory pathway and retrograde via the normal conduction system. Its morphology is a regular, wide-complex QRS tachycardia (often difficult to distinguish from ventricular tachycardia), as the QRS complexes exhibit maximal preexcitation.
Tachycardias Generated Outside the Circuit:
These are atrial tachyarrhythmias generated independently of the Wolff-Parkinson-White circuit (atrial fibrillation, atrial flutter, or atrial tachycardia) that conduct to the ventricles via the accessory pathway.
Because the pathway lacks the decremental conduction properties of the AV node, it can conduct at dangerously high ventricular rates and degenerate into ventricular fibrillation.
Other Types of Preexcitation: Lown-Ganong-Levine Syndrome
This syndrome has fallen out of clinical use as its electrophysiological mechanism has not been validated. Currently, its use as a clinical diagnosis is discouraged.
Lown-Ganong-Levine syndrome was described in 1952 and was historically considered secondary to an accessory pathway connecting the atrium directly to the distal AV node.
This allowed the impulse to bypass the physiological delay of the AV node and depolarize the bundle of His prematurely, with subsequent ventricular activation continuing via the normal His-Purkinje system.
The historically described EKG features of Lown-Ganong-Levine are:
- Normal P wave.
- Short PR interval.
- Normal QRS complex.
- Normal T wave.
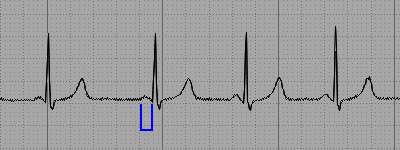
Lown-Ganong-Levine: short PR interval (blue), with no other alterations
In summary, the EKG in Lown-Ganong-Levine syndrome is characterized by a isolated short PR interval with an otherwise normal tracing.
References
- 1. Brugada J, Katritsis DG, Arbelo E, et al. 2019 ESC Guidelines for the management of patients with supraventricular tachycardia
The Task Force for the management of patients with supraventricular tachycardia of the European Society of Cardiology (ESC): Developed in collaboration with the Association for European Paediatric and Congenital Cardiology (AEPC). Eur. Heart J. 2020; 41(5): 655–720. doi: 10.1093/eurheartj/ehz467.
- 2. Krahn AD, Manfreda J, Tate RB, et al. The natural history of electrocardiographic preexcitation in men: the Manitoba Follow-up Study. Ann Intern Med. 1992; 116: 456–460. doi: 10.7326/0003-4819-116-6-456.
- 3. Vidaillet HJJ, Pressley JC, Henke E, et al. Familial occurrence of accessory atrioventricular pathways (preexcitation syndrome). N Engl J Med. 1987; 317: 65–69. doi: 10.1056/NEJM198707093170201.
- 4. Surawicz B, Deal BJ et al. AHA/ACCF/HRS Recommendations for the Standardization and Interpretation of the Electrocardiogram Part III: Intraventricular Conduction Disturbances. J Am Coll Cardiol. 2009; 53(11): 976-981. doi: 10.1016/j.jacc.2008.12.013.
- 5. Page RL, Joglar JA, Caldwell MA,et al. 2015 ACC/AHA/HRS Guideline for the Management of Adult Patients With Supraventricular Tachycardia: Executive Summary: A Report of the American College of Cardiology/American Heart Association Task Force on Clinical Practice Guidelines and the Heart Rhythm Society. Circulation. 2015; 133(14). doi: 10.1161/CIR.0000000000000310.